Acknowledging Negative Feedback Helps Hospitals Recover Dissatisfied Patients
Human Review Confirms That the Concern Requires Service Recovery
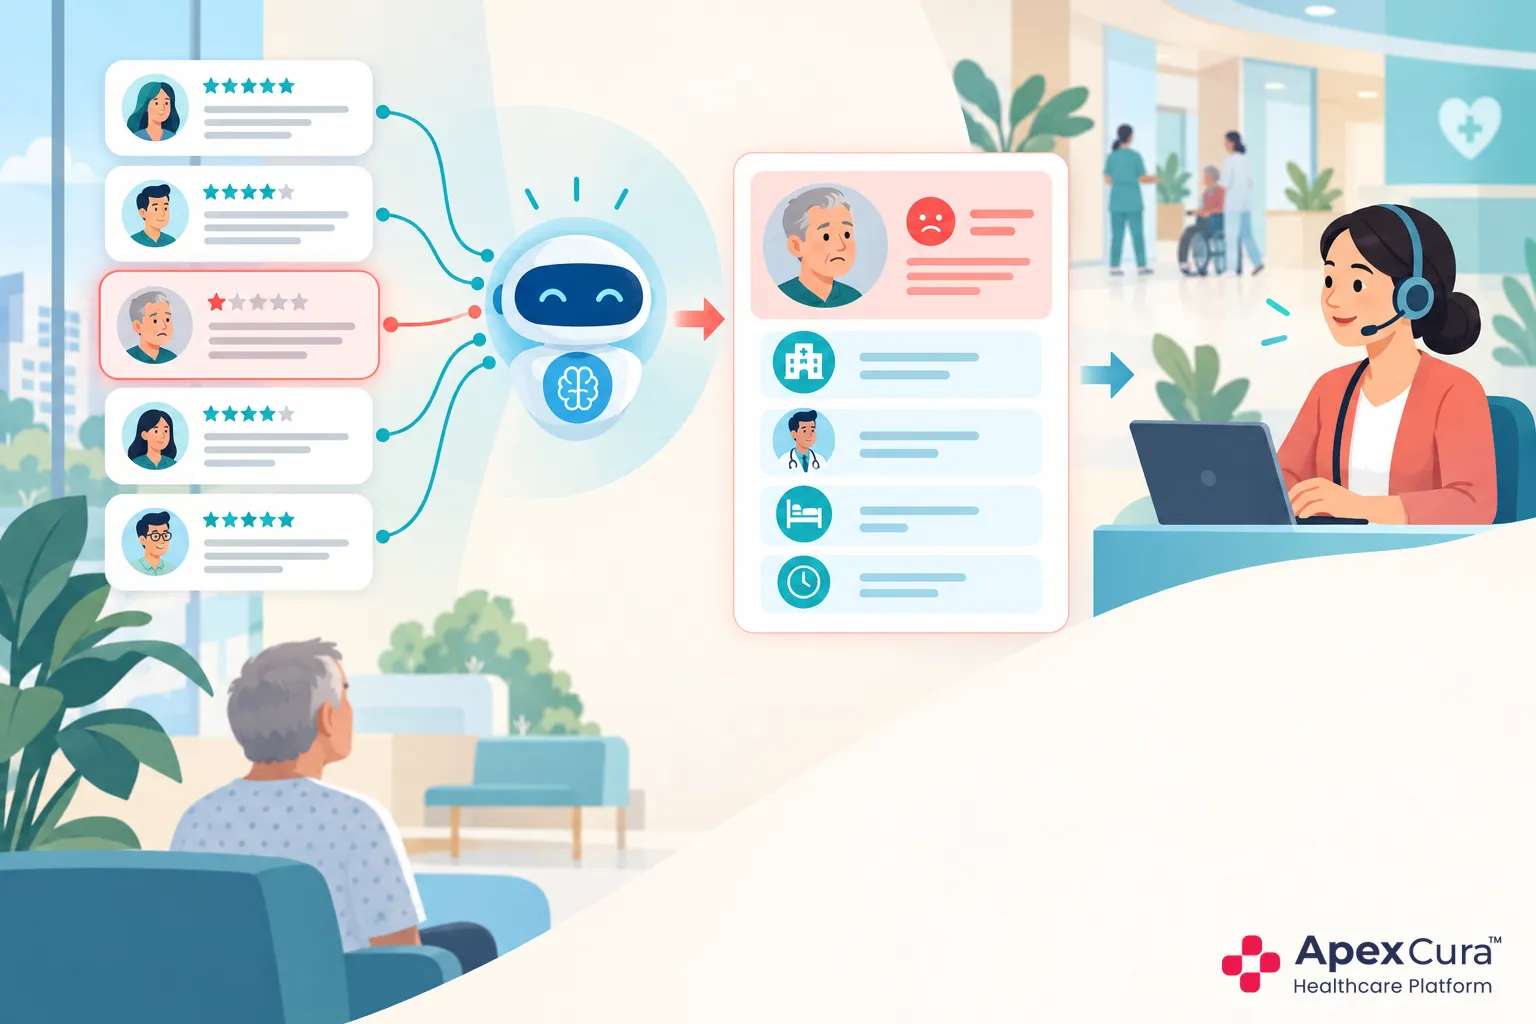
A low score or negative comment may create a potential recovery case, but a person should review the response before action begins. The reviewer checks whether the feedback relates to the recorded visit, whether the concern is understandable and whether it requires urgent contact or routine follow-up. Some comments may describe a misunderstanding, while others may report a serious service failure. Human review prevents a keyword or score from deciding the response on its own. It also allows the hospital to consider patient vulnerability, the service involved and any immediate risk before setting the priority and assigning the case. A separate guide explains how AI identifies dissatisfied patients before human review.
Patient Acknowledgement Confirms That the Concern Was Received
Acknowledgement should be clear and proportionate. The hospital can confirm that the feedback was received, identify who will review it and explain when the patient can expect the next update. This is not the stage for a defensive explanation or an unverified promise. A patient who reported unclear billing may first need assurance that the billing team will examine the account. A patient who described staff behaviour may need a named contact and a private conversation. Prompt acknowledgement reduces uncertainty and establishes that the concern has entered a responsible process rather than disappearing into a survey report. The acknowledgement should include a reference number when the hospital uses case tracking.
Case Priority Defines the Expected Response Time
Hospitals should not handle every negative response with the same urgency. A delayed meal, unclear signboard and allegation of disrespect require different response paths. Priority rules can consider the concern type, patient context, service stage and whether the issue is still affecting the patient. A current inpatient concern may need faster coordination than feedback received after discharge. The priority should set the expected first response, escalation point and review time. These rules help teams act consistently while still allowing authorised staff to raise or lower priority after speaking with the patient and reviewing the available information. Clinical-safety concerns should follow the hospital’s existing escalation policy immediately.
Clear Ownership Drives Investigation, Corrective Action and Patient Communication
Every Recovery Case Should Have an Owner and Response Timeline
A department may be responsible for the service, but a named owner is needed to move the case. The owner coordinates the review, records updates, contacts the patient or arranges the appropriate person to do so, and escalates delays. A response timeline prevents cases from staying open without progress. Cross-department concerns may need one coordinating owner even when billing, nursing and operations all contribute. Ownership does not mean deciding fault before investigation. It means one person remains accountable for bringing the necessary teams together and ensuring that the patient receives a clear update within the expected time. The named owner should remain accountable even when other departments support the investigation.
Patient Conversations and Service Records Help Clarify What Happened
The patient’s account is the starting point, not a complete operational diagnosis. The owner should understand what the patient expected, what they experienced and what outcome they are seeking. Relevant service records can then establish the sequence: appointment time, registration, billing, consultation, diagnostic activity or discharge steps. Staff may provide additional context, but the review should not become an exercise in disproving the patient. The aim is to identify the experience gap and the process behind it as accurately as possible. Where evidence remains unclear, the case record should state that uncertainty rather than present an assumption as fact.
Corrective Actions and Patient Conversations Should Remain Documented
A recovery record should show what was discussed, what the hospital agreed to do, who owns the action and when the next contact is due. If billing provides a clearer explanation, the case should record the explanation and any corrected document. If a department changes a handover, the action should describe the actual process change rather than say that staff were counselled. Documentation protects continuity when another employee takes over and helps management review overdue actions. It also separates a completed phone call from a completed recovery: speaking with the patient is one step, while addressing the confirmed concern is another.
Discuss how your hospital can assign, track and close service-recovery cases after negative feedback.
Discuss Hospital Service RecoveryDocumented Closure and Patient Follow-Up Complete the Recovery Process
Patient Communication Confirms the Action Taken
The final patient conversation should explain what the hospital reviewed, what action was taken and what could not be changed. The language should be direct and respectful, without claiming that every concern has a perfect solution. If the issue involved unclear discharge instructions, the team can provide the missing explanation and describe how the process is being corrected. If the hospital cannot confirm the patient’s interpretation, it can still explain the review and next step. The purpose is to close the communication gap, give the patient a clear outcome and record any remaining disagreement honestly. The message should avoid promises that the documented action cannot support.
Cases Close After Action and Communication Are Documented
A case should not close simply because its response deadline has arrived. Closure requires a documented review, completed action or recorded reason why action was not possible, and patient communication where appropriate. The closure status should distinguish resolved, partly resolved, no response, duplicate and other hospital-defined outcomes. Managers can then see whether teams are solving cases or only clearing queues. Some serious concerns may remain open through escalation even after an initial patient update. Clear closure criteria make service recovery measurable and prevent different departments from using the same status to mean completely different things. This prevents unresolved work from being hidden by an administrative status change.
Follow-Up Confirms Whether the Patient Believes the Concern Was Resolved
A short follow-up can confirm whether the patient understood the action and believes the concern was addressed. It should not pressure the patient to withdraw feedback or provide a better rating. The response may show that the practical issue was fixed but communication remains incomplete, or that the patient accepts the explanation even though the original experience cannot be changed. Hospitals can use this outcome to improve recovery practice and identify concerns that recur after closure. A structured hospital service-recovery workflow supports ownership and visibility, while hospital teams remain responsible for judgement, conversation and resolution. The follow-up outcome should be recorded against the same recovery case.
Conclusion
Hospitals can recover dissatisfied patients when negative feedback receives acknowledgement, clear ownership and timely action. The recovery team must understand the patient’s concern, verify the relevant service records, communicate what the hospital can do and document every action. A case should close only after the action and patient communication are recorded. Follow-up then helps the hospital understand whether the patient believes the concern was resolved. This disciplined process turns negative feedback into accountable service recovery instead of another unresolved entry in a report.