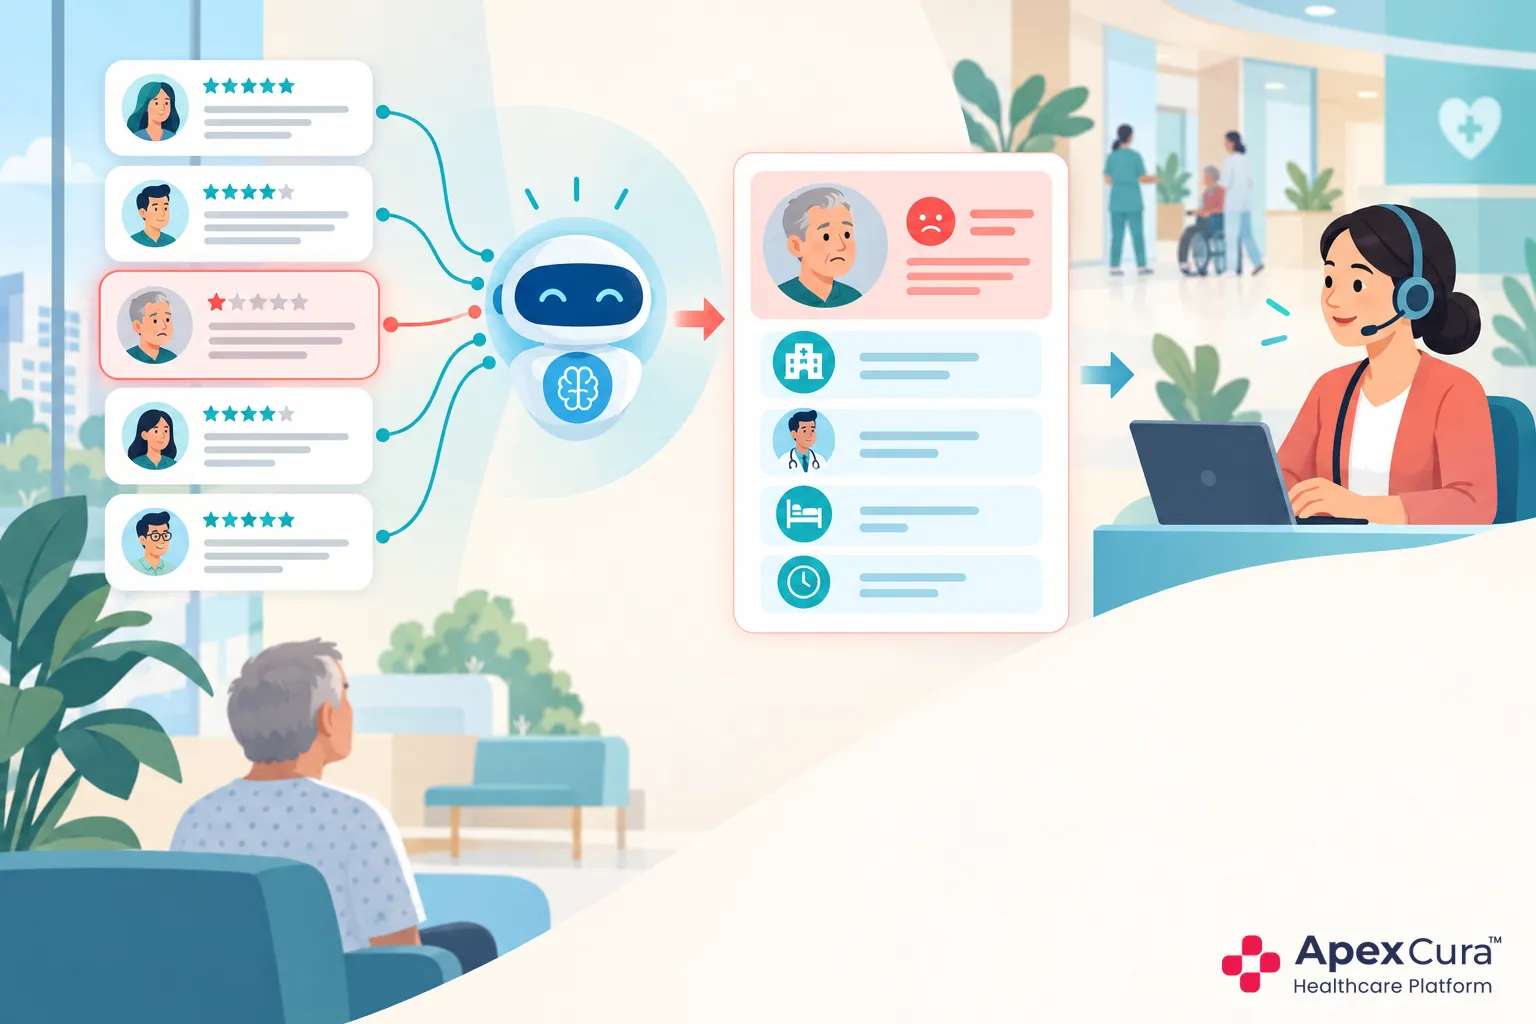
Feedback Collection Alone Does Not Improve Patient Experience
Feedback Scores Show the Experience, Not the Operational Cause
A low rating tells management that a patient had a poor experience, but it does not explain what created it. A patient who reports long OPD waiting may have faced delayed registration, a doctor starting late, a billing hold or weak delay communication. The score identifies where the hospital should look; it does not prove which process failed. Teams must review the comment, visit stage and available operational records before deciding the cause. Acting on the score alone can produce the wrong correction, such as adding front-desk staff when the actual delay began after billing. Timestamps from registration, consultation and billing help test each possibility.
Feedback Without Journey Context Gives an Incomplete Picture
The same rating means different things depending on where the patient was in the hospital journey. A score after an OPD consultation may relate to registration, waiting, doctor communication or diagnostics. A discharge response may concern nursing communication, bill explanation, medicines or the time taken to leave. Hospitals need the branch, department, service, doctor and patient event attached to the response. Without this context, a central team may forward a concern to the wrong department or combine unrelated experiences into one report. Journey context makes feedback useful without assuming that it proves the cause. The review should retain the encounter number so teams examine the correct visit.
Feedback Without Ownership and Action Remains a Report
Many feedback reviews end with a presentation of average scores and a list of negative comments. Improvement begins only when a concern receives an owner, an action and a review date. A repeated discharge-communication issue may belong to the inpatient operations team, while unclear bill explanations may require billing leadership. Management should record who will examine the issue, what will change and when the result will be reviewed. Otherwise, the same concern returns in the next report with no evidence that anyone acted. Collection creates visibility; accountable follow-through creates the possibility of improvement. A weekly action register prevents agreed work from disappearing after the meeting.
Hospitals Should Proactively Measure, Understand and Act on Patient Feedback
Measure Feedback After OPD, Diagnostics and IPD Discharge
Hospitals should decide which patient events need regular measurement instead of sending one generic survey to everyone. OPD feedback can examine registration, waiting, consultation and coordination. Diagnostic feedback can cover instructions, staff interaction and report communication. IPD discharge feedback can examine nursing communication, bill clarity and discharge readiness. Questions should match the experience being measured, and the same definitions should be used over comparable periods. The objective is not to ask after every small activity. It is to collect enough structured feedback at relevant points to show where patient experience needs management attention. Each survey should remain short enough for patients to complete on a phone.
Compare Feedback Across Doctors, Departments and Branches
A hospital-wide average can hide a local problem. Two branches may have the same overall score while one receives repeated billing concerns and the other receives comments about discharge communication. Doctor-level comparisons also need similar visit types, adequate response volume and patient comments; one score should never become a simple ranking. Management should compare like with like: OPD with OPD, discharge with discharge, and similar periods with similar periods. The useful question is not who has the highest score. It is where a consistent difference appears, what patients are reporting and which team should investigate it. Compare response counts as well, because small samples can create misleading differences.
Route OPD Waiting Concerns to Operations and Discharge Concerns to Inpatient Teams
Feedback becomes actionable when each concern reaches the team that can examine it. OPD waiting comments may go to operations for review against registration, billing, doctor-start and queue information. Discharge concerns may go to the inpatient team to examine counselling, medicine instructions, final billing and discharge coordination. The receiving team should see the original comment and relevant visit context rather than a shortened complaint label. Routing does not establish blame. It places the concern with people who can compare the patient’s account with the process, speak with staff and define a suitable corrective action. The owner should acknowledge receipt so the concern is not left between teams.
Discuss how your hospital can connect patient feedback with defined actions and regular outcome reviews.
Discuss Patient Experience ManagementDefined Actions and Outcome Reviews Drive Continuous Patient Experience Improvement
Assign Discharge-Communication Issues to Inpatient Teams With a Review Date
A useful action is specific enough to review. If patients repeatedly say that discharge instructions are unclear, assigning the issue to the inpatient team is only the first step. The team may standardise who explains medicines, when the family receives instructions and how unanswered questions are recorded. Management should set a review date and define what later evidence will be examined, such as comments about medicine clarity or discharge readiness. This turns a broad instruction to improve communication into a practical process change with an owner, expected behaviour and a date for checking the result. The action register should name the responsible lead, not only the department.
Compare Later Feedback to Check Whether Discharge Communication Improved
Closing an action does not show that the patient experience improved. After changing the discharge explanation process, the hospital should review later feedback from comparable discharged patients. Teams can examine whether the same concern appears less often, whether comments describe clearer instructions and whether the response volume is large enough to interpret. They should also check that the questions and collection method remained consistent. A better score may be encouraging, but the comments and journey context show whether the change addressed the intended issue. Outcome review protects hospitals from declaring success after completing an activity rather than improving an experience. Reviewers should use the same patient group and reporting period for comparison.
Retain, Revise or Expand Actions Based on Reviewed Results
A hospital can retain an action when later feedback shows a consistent improvement, revise it when the concern continues, or stop it when it creates no useful change. An effective discharge checklist in one department may be tested in another before being adopted across the hospital group. A weak intervention may need a different owner, clearer staff training or a process change elsewhere. This repeatable cycle—measure, understand, act and review—is the basis of proactive experience management. A structured patient feedback management system can support the evidence and accountability, while hospital leadership remains responsible for the decisions. Leadership should record the decision so the next review starts with evidence.
Conclusion
Hospitals improve patient experience consistently when feedback becomes part of a regular management process. Scores and comments must retain enough journey context for teams to understand the concern, assign an owner and define a practical action. The hospital should then review feedback from comparable patients to see whether the change worked. This cycle helps management retain effective actions, revise weak ones and expand improvements carefully across departments or branches. Patient feedback creates value when hospitals use it to make decisions and verify outcomes.