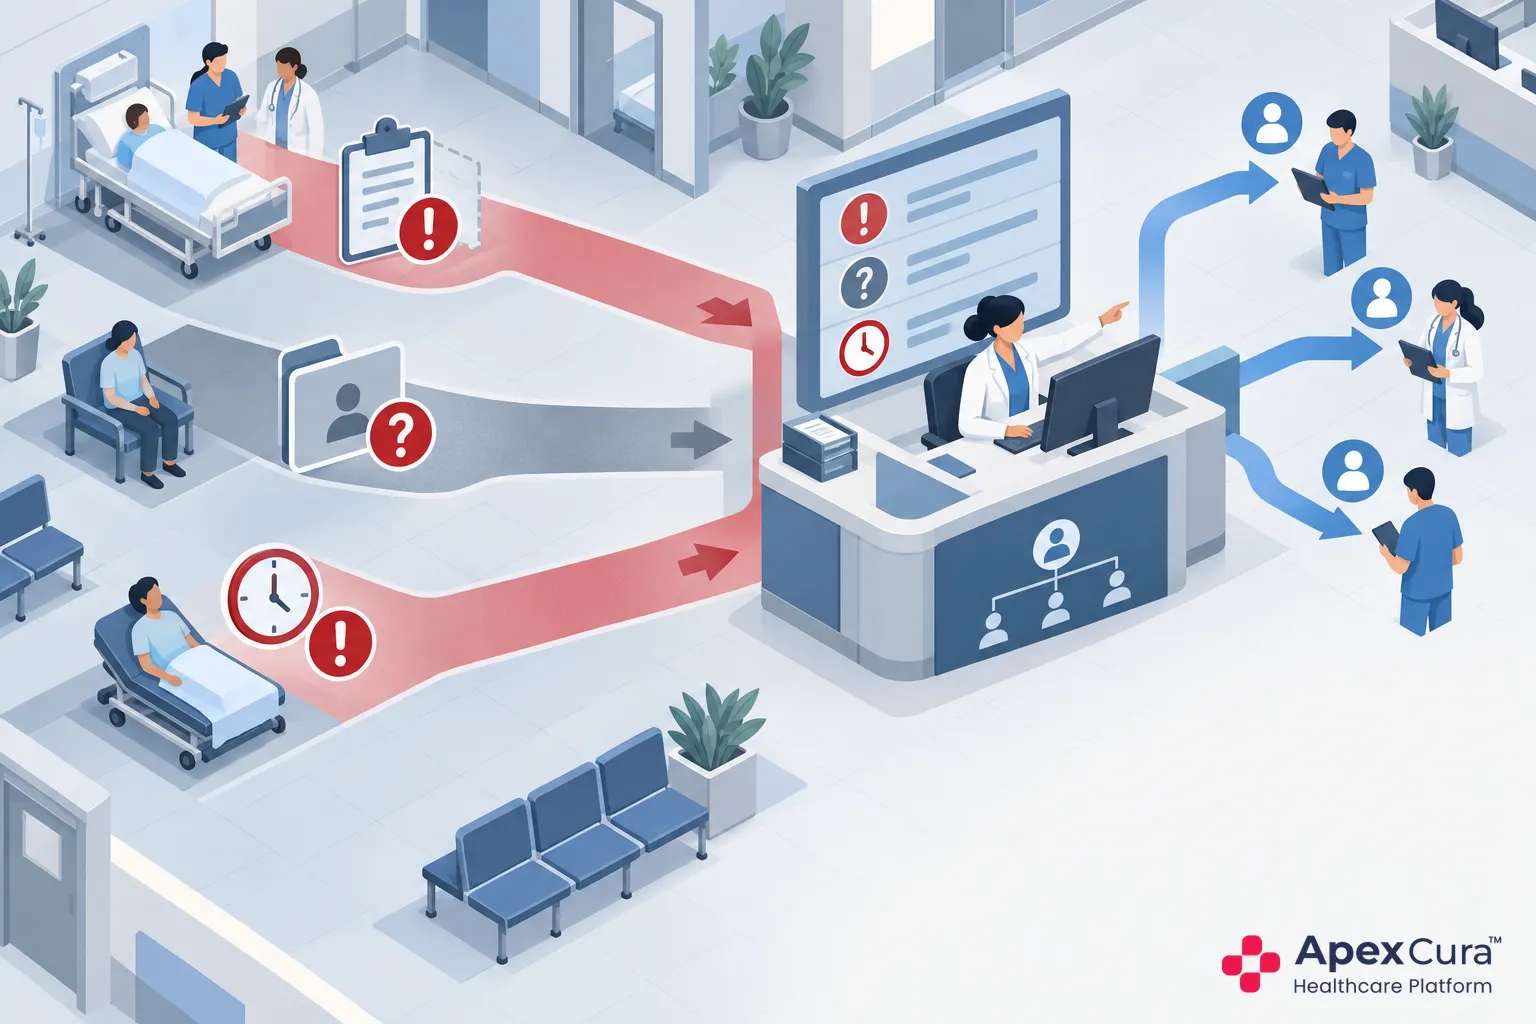
Doctor Recommendation Tracking Begins During the OPD Consultation
Admission, Surgery and Revisit Recommendations Need Separate Classification
Admission, surgery and revisit advice lead to different actions and should not be placed under one generic follow-up label. An admission recommendation may need immediate counselling about the next hospital step. A planned surgery may require medical and cost clarification. A revisit recommendation needs a future appointment or confirmation that the patient returned. Separate classification gives the counselling team the right starting point and prevents a revisit patient from being counted in an OPD-to-IP conversion denominator. The doctor remains responsible for the clinical recommendation; the tracking process records what happens after it. The classification should remain visible in worklists and reports so teams do not compare unlike recommendation journeys.
Patient, Doctor, Speciality and Branch Details Establish the Context
The recommendation record should retain the patient, consulting doctor, speciality, branch, consultation date and advised service. These details help the receiving team understand where the recommendation came from and route it correctly. They also prevent duplicate cases when the same patient has more than one visit or recommendation. The record should use verified hospital data rather than asking counsellors to rebuild the context from memory. Where clinical clarification is required, the recommendation must remain linked to the treating team so the patient receives an authorised answer. The encounter number and recommendation timestamp also help staff distinguish repeat visits and identify the correct clinical record.
Structured Capture Reduces Dependence on Prescriptions and Verbal Handovers
A prescription can record clinical advice but it is not a shared operational worklist. Verbal handovers depend on the right person being available and remembering the details. Structured capture creates a visible case that can be assigned, reviewed and updated. For example, an admission recommendation recorded at 11:30 am should be visible to the counselling team even if the doctor’s assistant changes shifts. The original prescription remains part of the clinical record; recommendation tracking provides the accountable handover needed for counselling and follow-up. A shift-end reconciliation can compare recorded recommendations with counselling cases and identify any advice that did not enter the worklist.
Every Treatment Recommendation Needs Counsellor Ownership and a Current Status
Each Recommendation Should Be Assigned to a Responsible Counsellor
Assignment should happen through a clear hospital rule, such as branch, speciality, service line or available team member. The assigned counsellor becomes responsible for reviewing the case and starting the appropriate conversation. Supervisors should be able to see the assigned workload and move cases when someone is unavailable. Ownership does not mean one person must answer every question. It means one person coordinates the case and ensures that questions reach the treating, billing or operations team instead of leaving the patient to contact multiple departments independently. An assignment timestamp and visible acceptance status help supervisors identify cases that were routed but never taken up.
Counselling Status Should Show Whether the Conversation Is Awaiting, Started or Completed
A simple current status helps teams understand what has happened without reading every note. Awaiting counselling means the case is assigned but the first conversation has not started. Started means the team has spoken with the patient but information or a decision is still pending. Completed means the required counselling has been delivered, although the patient may still need time to decide. Hospitals should define these terms consistently. If every counsellor uses a different meaning for completed, management cannot identify cases that genuinely need attention. Each status change should carry a date, responsible user and short note so the next team member understands the progress.
Current Status Should Guide the Required Follow-Up
The next action should follow from the status. A case awaiting counselling needs the first contact or in-person handover. A started case may need a doctor clarification, estimate, family discussion or scheduled callback. A completed counselling case may need only a decision check at the time agreed with the patient. This prevents teams from calling every patient in the same way. It also allows supervisors to distinguish an operational delay from a patient who has received the required information and requested time. For example, a case waiting for an estimate needs billing action before another patient call is scheduled unnecessarily.
Discuss how your hospital can capture and track every doctor recommendation until the patient reaches a decision.
Discuss Recommendation TrackingHospital Recommendation Follow-Up Continues Until the Patient Decides
Pending Recommendations Need a Follow-Up Owner and Date
Pending is a temporary state, not an outcome. Every pending recommendation should state why it is pending, who owns the next action and when that action is due. A patient waiting for a medical clarification should not receive the same follow-up as a patient waiting for family approval. The owner should check whether the hospital completed its promised action before contacting the patient again. This creates respectful follow-up and exposes cases where an internal delay, rather than the patient, is holding up the decision. Due and overdue views help supervisors identify missed actions without treating every older case as a patient delay.
Every Follow-Up Should Update the Recommendation Status
A contact attempt should add useful information. The record should show whether the patient was reached, what changed, which concern remains open and what happens next. Repeating “follow-up done” does not help another counsellor understand the case. When admission recommendations fail to reach initial counselling, hospitals need a more specific exception view. The admission recommendation tracking article explains how incomplete handovers, unassigned cases and delayed first actions can be identified separately from normal pending decisions. An unanswered call should record the attempt and next date, while a completed conversation should capture the patient response and remaining concern for team continuity.
Proceeding, Postponed, Declined and No-Response Outcomes Need Documentation
The final status should reflect the patient’s actual decision. Proceeding may lead to admission, surgery scheduling or a planned revisit. Postponed should include the expected review point when known. Declined should record the verified reason without turning the note into a judgement about the patient. No response should be used only after the hospital completes its defined contact effort. Consistent outcome recording allows the Patient Financial Counselling team to review recommendation coverage while protecting patient choice and avoiding inflated conversion claims. The record should also show the decision date and verified reason so later reports do not depend on assumptions or memory.
Conclusion
Doctor recommendation tracking closes the operational gap between clinical advice and patient action. Hospitals should capture admission, surgery and revisit recommendations during the OPD journey, assign them to a responsible counsellor and maintain a meaningful status. Follow-up should respond to the actual pending reason and continue until the patient proceeds, postpones, declines or remains unreachable after the defined effort. This creates accountable handover and reliable recommendation visibility without interfering with clinical judgement or the patient’s right to decide.